Not an actual AS or nr-axSpA patient
AS and nr-axSpA patients met ASAS40 at Week 14 (primary endpoint) and disease control through ASDAS low disease activity at Week 14 (ranked secondary endpoint), with responses observed up to 2 years.1,3-7
AS and nr-axSpA patients met ASAS40 at Week 14 (primary endpoint) and disease control through ASDAS low disease activity at Week 14 (ranked secondary endpoint), with responses observed up to 2 years.1,3-7
Not an actual AS or nr-axSpA patient
AS=ankylosing spondylitis; ASAS=Assessment of SpondyloArthritis international Society; ASAS40=≥40% improvement and an absolute improvement from baseline of ≥2 units on a scale of 0 to 10 in at least 3 of the 4 domains, with no worsening in the fourth domain: total back pain, inflammation (mean score of BASDAI questions 5 and 6 on severity and duration of morning stiffness), physical function (BASFI), and patient global assessment of disease activity; ASDAS=Ankylosing Spondylitis Disease Activity Score; BASDAI=Bath Ankylosing Spondylitis Disease Activity Index; BASFI=Bath Ankylosing Spondylitis Functional Index; bDMARD=biologic disease-modifying antirheumatic drug; IR=intolerance or inadequate response; NPA=National Prescription Audit; nr-axSpA=non-radiographic axial spondyloarthritis; NSP=National Sales Perspectives; TNFi=tumor necrosis factor inhibitor; tsDMARD=targeted synthetic disease-modifying antirheumatic drug
INDICATIONS
RINVOQ is indicated for the treatment of active ankylosing spondylitis (AS) in adults who have had an inadequate response or intolerance to one or more tumor necrosis factor (TNF) blockers.
RINVOQ is indicated for the treatment of active non-radiographic axial spondyloarthritis (nr-axSpA) with objective signs of inflammation in adults who have had an inadequate response or intolerance to TNF blocker therapy.
Limitations of Use: RINVOQ is not recommended for use in combination with other Janus kinase (JAK) inhibitors, biologic disease-modifying antirheumatic drugs (bDMARDs), or with potent immunosuppressants such as azathioprine and cyclosporine.
*Primary endpoint.
†Ranked secondary endpoint.
‡As of 08/2025: in RA, ~9.5 years maximum exposure (~4.2 years median) to RINVOQ 15 mg; in PsA, ~6.4 years maximum exposure (~3.6 years median) to RINVOQ 15 mg.8
§RINVOQ is on a preferred tier or otherwise has preferred status on the plan's formulary.
||Coverage requirements and benefit designs vary by payer and may change over time. Please consult with payers directly for the most current reimbursement policies.
AS=ankylosing spondylitis; ASAS=Assessment of SpondyloArthritis international Society; ASAS40=≥40% improvement and an absolute improvement from baseline of ≥2 units on a scale of 0 to 10 in at least 3 of the 4 domains, with no worsening in the fourth domain: total back pain, inflammation (mean score of BASDAI questions 5 and 6 on severity and duration of morning stiffness), physical function (BASFI), and patient global assessment of disease activity; ASDAS=Ankylosing Spondylitis Disease Activity Score; BASDAI=Bath Ankylosing Spondylitis Disease Activity Index; BASFI=Bath Ankylosing Spondylitis Functional Index; LDA=low disease activity; nr-axSpA=non-radiographic axial spondyloarthritis; PsA=psoriatic arthritis; PY=patient-years; RA=rheumatoid arthritis; TNFi=tumor necrosis factor inhibitor
Please see Important Safety Information, including BOXED WARNING on Serious Infections, Mortality, Malignancies, Major Adverse Cardiovascular Events, and Thrombosis, below.
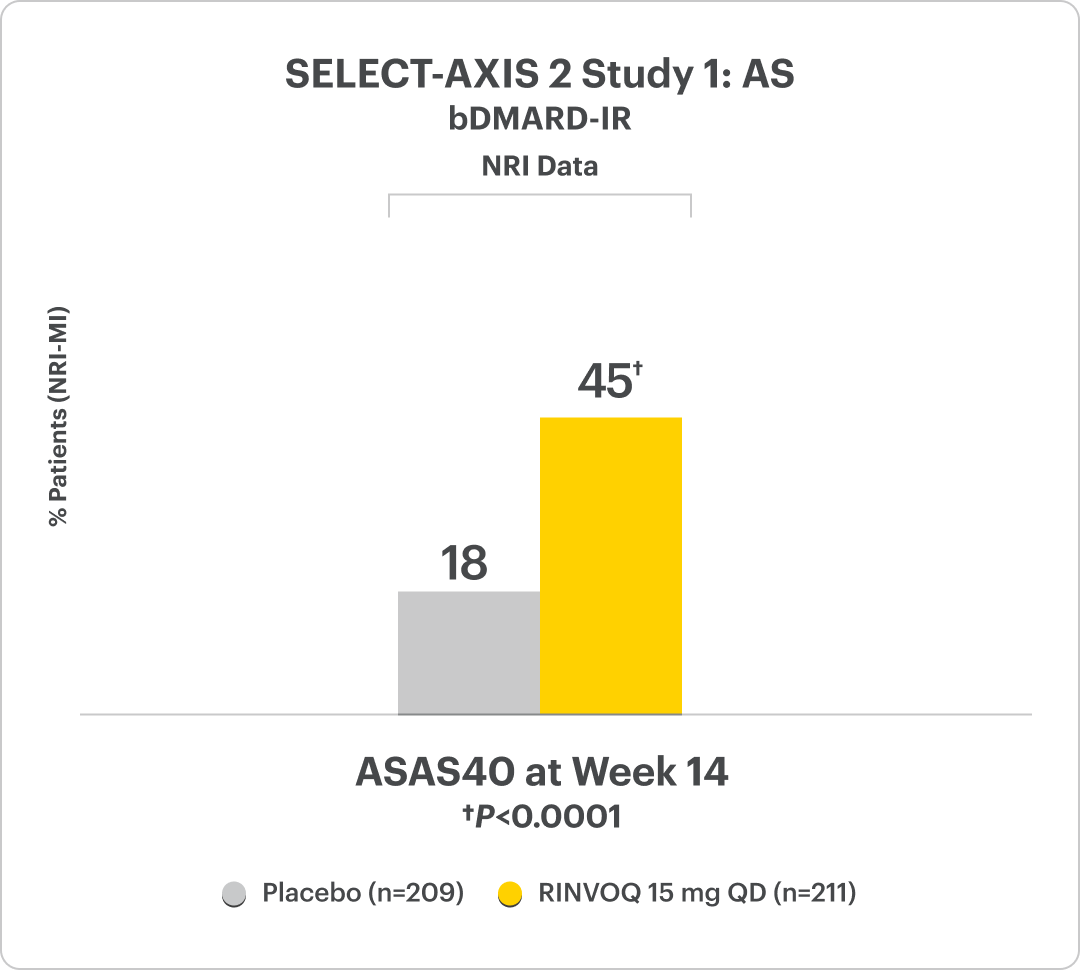
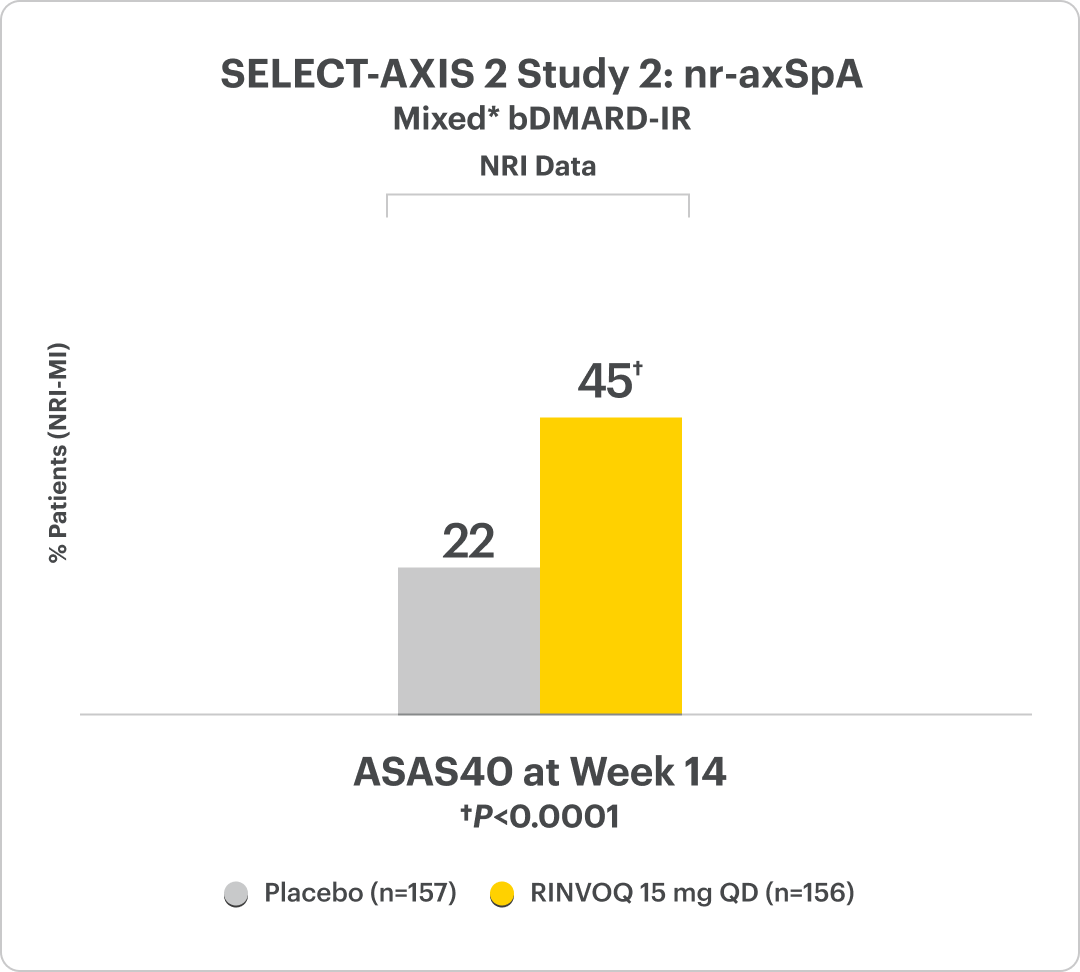
RINVOQ Met Its Primary Endpoint of ASAS40 at Week 141,5,6
Rapid ASAS40 improvement at Week 14 with responses observed as early as Week 4 (AS) and Week 2 (nr-axSpA)
ASAS40 at Week 4 (AS):
22% RINVOQ vs 12% placebo5‡
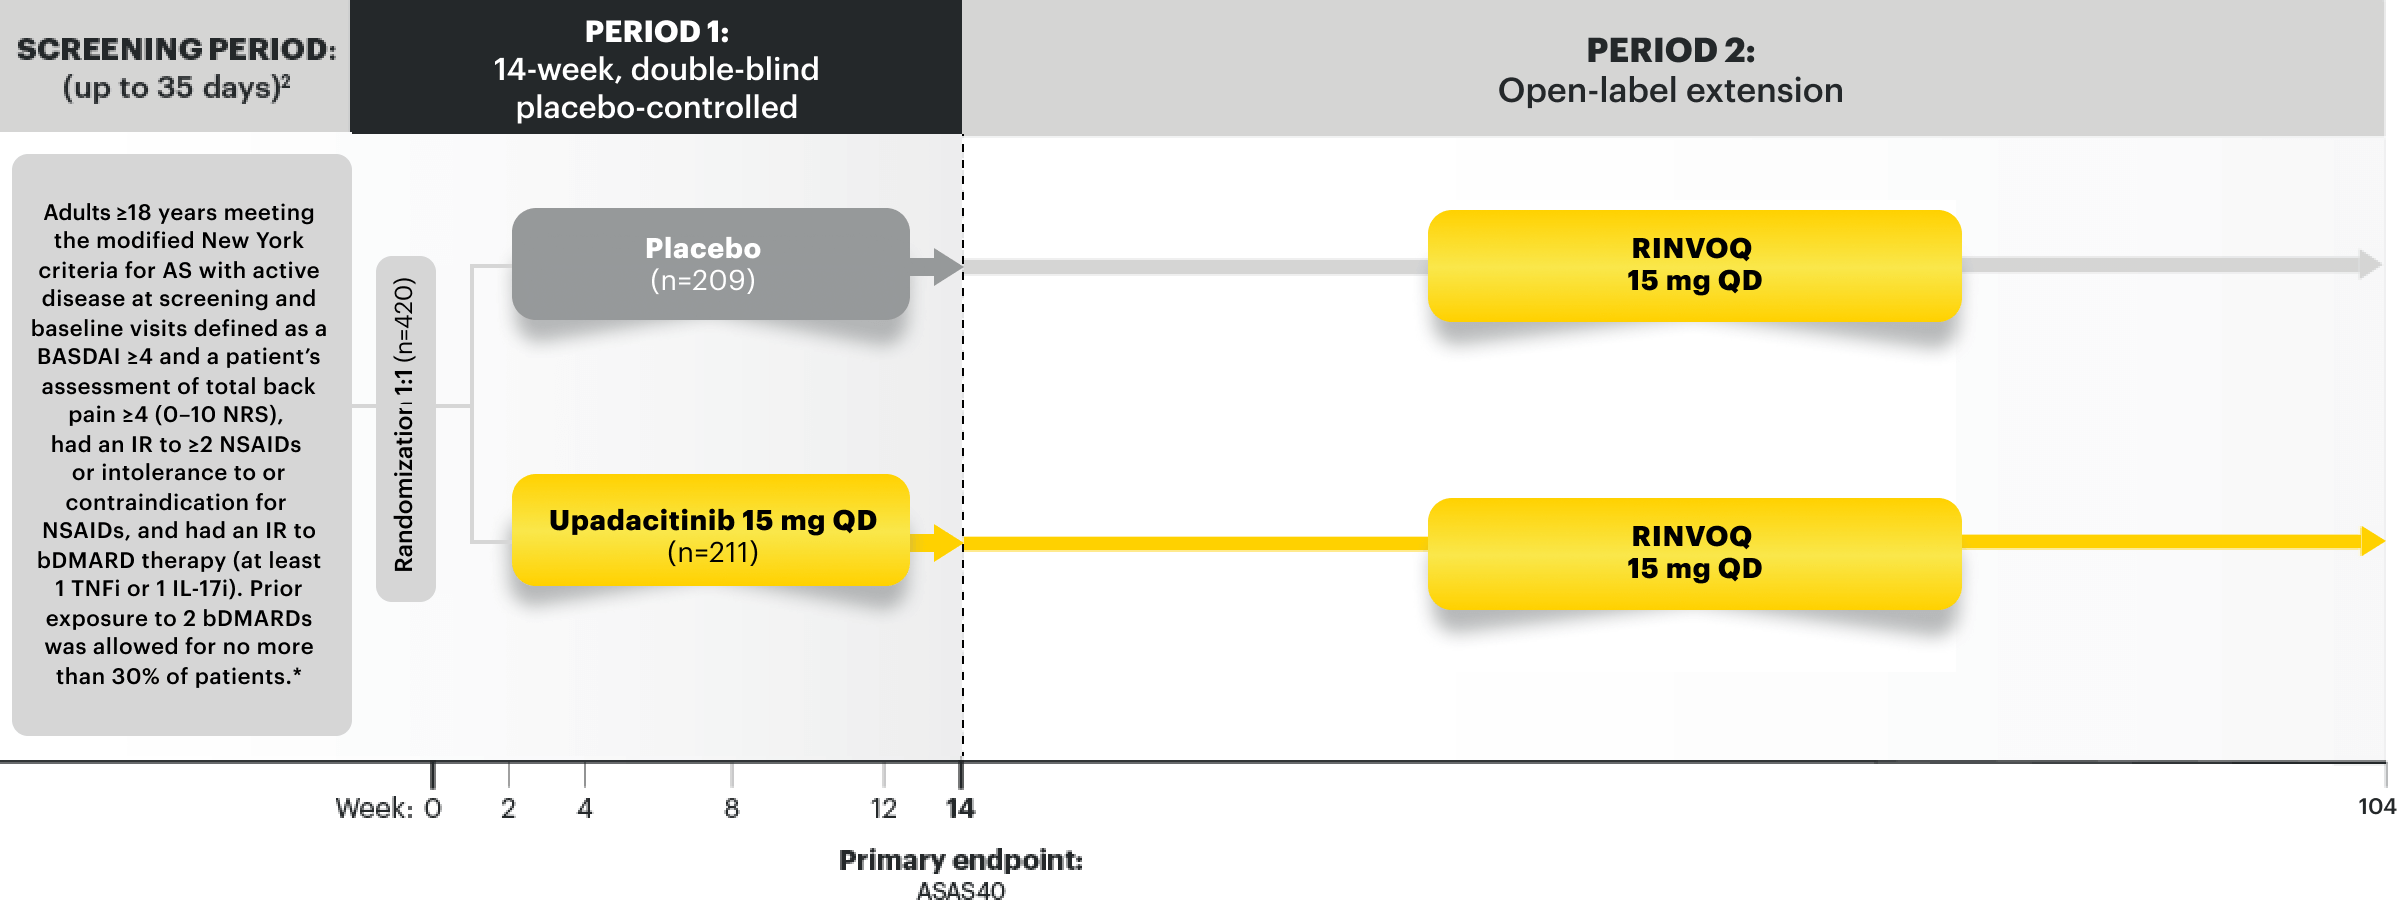
SELECT-AXIS 2 Study 1: AS Design Intro1,5:
14-week, double-blind, parallel-group, placebo-controlled Phase 3 study of 420 patients with active AS who had an intolerance or inadequate response to at least 2 NSAIDs and 1 or 2 bDMARDs. Patients were randomized to receive RINVOQ 15 mg once daily or placebo. Patients could continue background NSAIDs.
RINVOQ is indicated for TNFi-IR patients.
ASAS40 at Week 4 (AS):
22% RINVOQ vs 12% placebo5‡
SELECT-AXIS 2 Study 1: AS Design Intro1,5:
14-week, double-blind, parallel-group, placebo-controlled Phase 3 study of 420 patients with active AS who had an intolerance or inadequate response to at least 2 NSAIDs and 1 or 2 bDMARDs. Patients were randomized to receive RINVOQ 15 mg once daily or placebo. Patients could continue background NSAIDs.
ASAS40 at Week 2 (nr-axSpA):
12% RINVOQ vs 6% placebo7‡
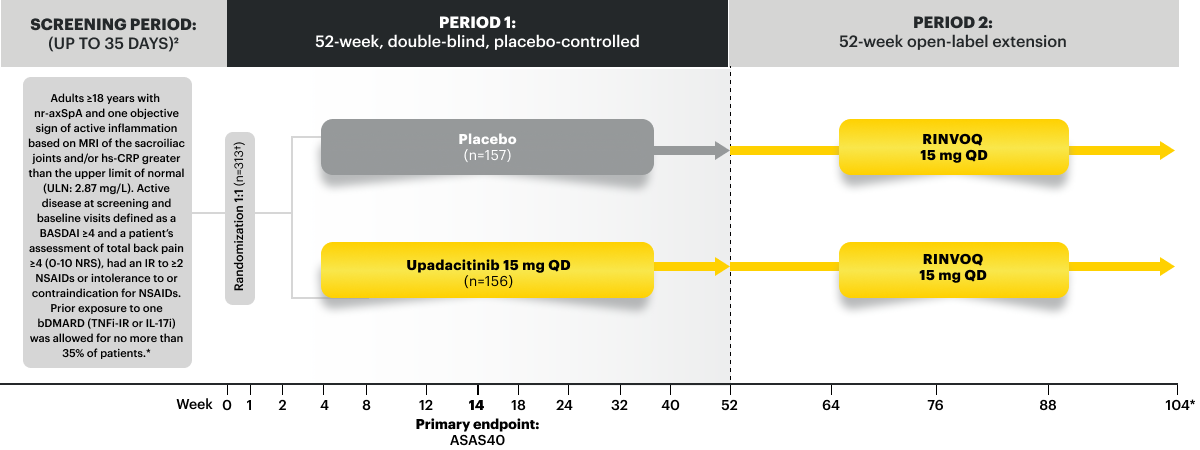
SELECT-AXIS 2 Study 2: nr-axSpA Design Intro1,6:
52-week, double-blind, placebo-controlled Phase 3 study of 313 patients with nr-axSpA and 1 objective sign of active inflammation based on MRI of the sacroiliac joints and/or hsCRP greater than the upper limit of normal (ULN; 2.87 mg/L). Patients had an intolerance or inadequate response to at least 2 NSAIDs and, in 33%, to 1 bDMARD. Patients were randomized to receive RINVOQ 15 mg once daily or placebo. Patients could continue background NSAIDs.
DATA LIMITATIONS: Data labeled as a primary endpoint at Week 14 were multiplicity-controlled. All other comparisons were not adjusted for multiplicity; therefore, statistical significance has not been established.
*Mixed=67% bDMARD-naïve & 33% bDMARD-IR.6
‡P<0.05; Analyses were not controlled for multiplicity; P-value obtained through nominal statistical testing.5,7
AS=ankylosing spondylitis; ASAS=Assessment of SpondyloArthritis international Society; ASAS40=≥40% improvement and an absolute improvement from baseline of ≥2 units on a scale of 0 to 10 in at least 3 of the 4 domains, with no worsening in the fourth domain: total back pain, inflammation (mean score of BASDAI questions 5 and 6 on severity and duration of morning stiffness), physical function (BASFI), and patient global assessment of disease activity; BASDAI=Bath Ankylosing Spondylitis Disease Activity Index; BASFI=Bath Ankylosing Spondylitis Functional Index; bDMARD=biologic disease-modifying antirheumatic drug; COVID-19=coronavirus disease-2019; hsCRP=high-sensitivity C-reactive protein; IR=intolerance or inadequate response; MRI=magnetic resonance imaging; nr-axSpA=non-radiographic axial spondyloarthritis; NRI=nonresponder imputation; NRI-MI=nonresponder imputation incorporating multiple imputation to handle missing data due to COVID-19; NSAID=nonsteroidal anti-inflammatory drug; QD=once daily; TNFi=tumor necrosis factor inhibitor; ULN=upper limit of normal